
Arthroscopy depends on a clear, stable view inside the joint. An Arthroscopy Pump helps regulate fluid flow and pressure while instruments move through small portals. The differences are practical: how pressure is controlled, how fluid enters, and whether outflow or suction is integrated. A steady view matters.
Common systems include gravity-fed setups, pressure-bag systems, and electronically controlled pumps. Some advanced units coordinate inflow and outflow, helping teams respond when instruments enter the joint or bleeding clouds the camera. The right choice depends on the procedure, anatomy, equipment compatibility, and the surgical team’s workflow. Higher pressure is not automatically better; excessive pressure can contribute to fluid escaping into surrounding tissues.
Market data offers useful context, but it needs careful interpretation. Grand View Research estimated the global arthroscopy devices market at approximately US$5.2 billion in 2023 and projected 6.2% annual growth from 2024 through 2030. That estimate covers a broad device category, not arthroscopy pumps alone. It signals commercial activity, not proof that one pump design improves outcomes. This distinction is easy to miss.
This guide compares the top types of arthroscopy pumps by control method, typical use, and practical trade-offs. It also considers setup demands and the limits of published market estimates. Product features vary, and clinical needs differ. A neat comparison cannot replace hands-on evaluation or the manufacturer’s instructions.
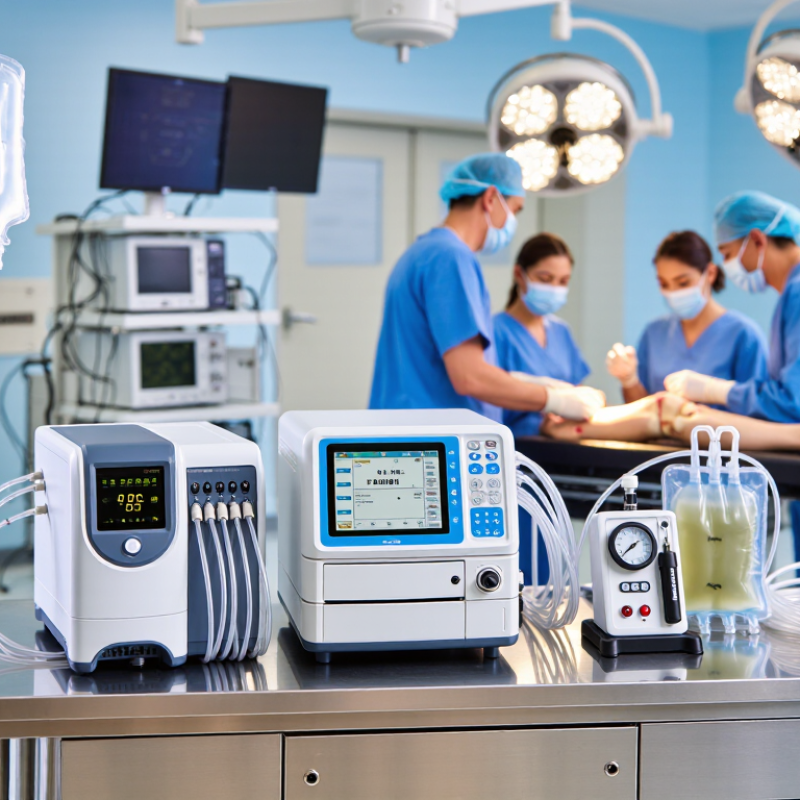
An arthroscopy pump does more than push saline into a joint. It balances pressure and flow so the surgeon can see tissue edges, instruments, and bleeding points. Many clinical reviews describe 40–60 mmHg as a practical starting pressure, adjusted for the joint and procedure. AORN’s 2024 Guidelines for Perioperative Practice also emphasize using the lowest effective pressure. The number is only a guide. A pressure display can look reassuring while the view still clouds if inflow is restricted or outflow is excessive.
Flow replaces fluid and clears debris; pressure helps keep the joint distended. Too little flow may leave blood and tissue particles in the field. Too much pressure can drive fluid into surrounding tissue, particularly during shoulder arthroscopy. A 2018 systematic review in Arthroscopy: The Journal of Arthroscopic and Related Surgery documented fluid extravasation among reported shoulder-arthroscopy complications, underscoring why pressure needs active monitoring.
Watch the tubing for kinks, the collection bag for flow changes, and the joint for swelling. Small adjustments often help. Still, pump readings do not tell the whole story; anatomy, portals, and outflow matter, too. That part is easy to overlook.
Gravity-fed arthroscopy pumps move irrigation fluid through elevation rather than a motorized pressure-control system. A fluid bag hangs above the joint, and gravity creates hydrostatic pressure as fluid travels down the tubing. Raising the bag increases the available pressure; lowering it reduces that driving force.
Simple, but not always predictable. Actual flow also depends on tubing resistance, the size of the access cannula, fluid viscosity, and how quickly fluid leaves the joint. For example, opening an outflow path can change the visible fluid level and joint distension. The bag’s height alone does not tell the whole story. Gravity-fed systems do not actively sense and correct pressure at the joint, so changes in the setup may require careful observation and adjustment.
This design can be useful when a straightforward, passive inflow method is appropriate. It also asks more of the surgical team: maintain a stable bag position, check connections, and watch for changes in visibility or joint fullness. That distinction matters. A clear view is helpful, but it is not a direct measurement of pressure. I would not treat a familiar setup as automatically consistent; small differences in height or tubing can still affect flow. Follow the procedure’s established monitoring practices and clinical protocol.
| Dimension | Typical characteristic | Practical implication |
|---|---|---|
| Inflow mechanism | Fluid flows from an elevated reservoir under gravity; hydrostatic head provides the driving pressure. | There is no pump actively sensing and regulating intra-articular pressure. |
| Pressure source | Pressure depends primarily on the vertical distance between the fluid surface and the joint, as well as fluid-line resistance. | Changing reservoir height changes the available hydrostatic pressure, but does not provide automatic pressure compensation. |
| Illustrative static head | For water-like fluid, 50 cm, 75 cm, and 100 cm of vertical head correspond to approximately 37, 55, and 74 mmHg, respectively. | These are theoretical static values; actual pressure at the joint can be lower during flow because of tubing, cannula, and outflow resistance. |
| Pressure adjustment | Typically adjusted by raising or lowering the reservoir and managing inflow or outflow pathways. | Adjustment is relatively simple, but changes are manual and may not respond immediately to changing surgical conditions. |
| Flow behavior | Flow varies with hydrostatic head, tubing configuration, cannula size, fluid viscosity, and resistance at the outflow path. | Flow and joint distension may fluctuate when instruments are inserted, outflow changes, or the reservoir level falls. |
| Equipment setup | Generally uses an elevated fluid bag or reservoir, tubing, and compatible inflow connections; it does not require a powered pressure-control unit. | Setup is comparatively straightforward, but reservoir positioning and secure suspension are important. |
| Potential advantages | Simple operating principle, no powered pressure-regulation mechanism, and straightforward visual monitoring of the fluid supply. | May suit procedures where basic gravity-driven irrigation is appropriate and the clinical team can manage inflow and outflow manually. |
| Limitations | No active pressure feedback; performance can vary as reservoir height, fluid level, and pathway resistance change. | Requires ongoing attention to joint distension and fluid egress. It may be less suitable when stable, actively regulated pressure is required. |
| Safety considerations | Pressure at the joint is not determined by reservoir height alone; anatomy, leakage, outflow, and procedure-specific factors also matter. | Use the device according to its instructions and the surgical team’s protocol; monitor the patient and joint throughout the procedure. |
Note: Hydrostatic pressure estimates are approximate and describe static head only. They are not recommended clinical pressure settings.
Pressure-controlled arthroscopy pumps regulate inflow as the knee fills and fluid escapes through the outflow cannula. Clinical knee-arthroscopy technique literature commonly describes 40–60 mmHg as a working irrigation range. It is not a universal target. AORN’s Guideline for Care of Patients Undergoing Arthroscopic Procedures emphasizes fluid management and monitoring during arthroscopy, rather than treating one pressure setting as suitable for every patient. The distinction matters: the pump’s displayed pressure may not equal pressure inside the joint.
At 40 mmHg, the view may remain clear when outflow is unobstructed. If the image clouds, a small adjustment can help—but higher pressure may also increase fluid extravasation into surrounding tissues. Check the tubing, cannula position, and outflow before raising the setting.
Small changes matter.
Patient anatomy, knee position, and leakage around portals can all affect performance. AORN guidance supports active monitoring, yet real-time judgment still has limits; visual clarity alone cannot show how much fluid has entered tissue. That part is easy to overlook. Use the lowest pressure that provides an adequate view, and follow local clinical protocols.
Flow-controlled arthroscopy pumps deliver irrigation at a selected rate, helping maintain a steady supply of fluid during a procedure. The pump meters flow through the inflow tubing rather than relying only on gravity. This can support a clear operative view as instruments move through the joint.
Small changes matter.
A set flow rate does not guarantee constant joint pressure. Pressure can rise when an instrument blocks an outlet or tissue restricts fluid escape. For that reason, clinicians monitor the pump display and the joint’s response, adjusting settings to the procedure and the patient. A clear view is useful, but excessive pressure is not a harmless trade-off.
Practical details affect performance. Staff should check tubing connections, prime the line, and look for kinks or leaks before use. During surgery, inflow and outflow need to work together; fluid balance also deserves attention. The setup is not always perfect. A sudden change in visibility may come from the pump, but it may also reflect a clogged cannula or shifting instrument position. That distinction takes observation, not guesswork.
Integrated inflow–outflow pumps coordinate saline delivery with fluid removal, helping maintain a clear view while limiting pooling around the scope. The balance is delicate. Too little outflow can cloud the image with blood and debris; excessive suction may collapse the working space or destabilize pressure. In shoulder arthroscopy, clinical literature commonly describes irrigation pressures around 40–60 mmHg, but these are reported practice ranges, not universal targets. Anatomy, procedure, and leakage all matter.
A 2024 Grand View Research report identifies fluid-management systems as a segment of the broader arthroscopy-device market and forecasts continued market growth through 2030. That commercial signal shows investment, not proof that one pump design improves outcomes. In use, an integrated system should let the team adjust inflow and outflow independently, watch the joint’s distension, and respond when the view suddenly clouds. A clear screen is useful, but it is not a pressure gauge. I would be cautious about relying on preset values alone: tissue swelling and fluid extravasation can develop even when the display looks steady. The awkward part is that no single setting suits every joint.
This functional comparison shows the core role of each pump type: inflow pumps deliver irrigation fluid, outflow pumps remove it, and integrated systems manage both. Coordinating inflow and outflow can help maintain joint distension and a clear surgical view. Actual features vary by system.
Nexia Medical
2255 Glades Rd
Boca Raton, FL 33431
Copyright 2017 Nexia Medical | All Right Reserved.